The combination of high blood pressure and type 2 diabetes deserves particular attention because both conditions can affect blood vessels and increase the risk of complications involving the heart, kidneys, eyes, and other organs.
Both conditions can affect blood vessels through different mechanisms. Persistently elevated blood glucose can damage small blood vessels over time, while high blood pressure places additional strain on artery walls and the cardiovascular system.
This is an important point as both conditions can cause damage to your vessels. High blood glucose levels can cause damage to small vessels over time and high blood pressure can cause extra strain on the arteries and cardiovascular system.
If you have both type 2 diabetes and hypertension, managing blood glucose alone is not enough. You will need to manage your blood pressure, cholesterol, kidney function and other cardiovascular risk factors.
We will look at how high blood pressure and type 2 diabetes interact, what complications you should be aware of, what target blood pressures may be and how to safely manage both conditions.
Article Index
- Why High Blood Pressure Is Common in Type 2 Diabetes
- How Hypertension Increases Diabetes Complications
- How High Blood Pressure Affects the Heart and Blood Vessels
- The Connection Between Hypertension and Diabetic Kidney Disease
- How High Blood Pressure Can Affect the Eyes and Other Blood Vessels
- Insulin Resistance and Hypertension: Understanding the Connection
- What Blood Pressure Target Should People With Diabetes Aim For?
- How to Monitor Blood Pressure at Home
- Managing Type 2 Diabetes and Hypertension Together
- Frequently Asked Questions
- Key Takeaways
Why High Blood Pressure Is Common in Type 2 Diabetes
High blood pressure is common in people with type 2 diabetes. Several contributing factors overlap such as being overweight, lack of exercise, insulin resistance and certain eating/lifestyle choices.
However, just because you have diabetes doesn’t mean you will automatically get high blood pressure.
Several factors are associated with an increased likelihood of developing type 2 diabetes and high blood pressure:
Insulin resistance: When the body’s cells become less responsive to insulin, the pancreas may produce more insulin to compensate. Insulin resistance is associated with metabolic changes that can also contribute to elevated blood pressure.
Obesity: Carrying excess body fat can increase the workload on the cardiovascular system and contribute to insulin resistance.
Lack of physical activity: Physical inactivity can contribute to reduced cardiovascular fitness, weight gain, and insulin resistance.
Diet: Regularly consuming foods high in sodium can contribute to elevated blood pressure, particularly in people who are salt-sensitive.
Older age and family history: As you get older you are more likely to get hypertension and type 2 diabetes. Genetics can play a role in these diseases.
Hypertension is an important risk factor for development of atherosclerosis-related cardiovascular disease, heart failure and microvascular complications in patients with diabetes (American Diabetes Association [ADA]).
As such it is common practice for health professionals to routinely monitor blood pressure alongside blood glucose and other cardiovascular risk factors.
How Hypertension Increases Diabetes Complications
Why is high blood pressure a concern for people with type 2 diabetes?
Having high levels of glucose in the blood over a long period can cause damage to the lining and function of your blood vessels. When you also have high blood pressure this puts extra strain on your blood vessels.
This can increase your risk of complications.
Damage to small blood vessels
Small blood vessels provide oxygen and nutrients to organs such as the kidneys, eyes, and nerves.
These can be damaged by diabetes causing complications such as kidney disease and retinopathy.
When hypertension is also present, the additional vascular strain may increase the risk of damage to these small blood vessels and contribute to complications.
Damage to larger arteries
High blood pressure can contribute to changes in the walls of larger arteries and increase the risk of atherosclerosis.
Atherosclerosis is a condition in which fatty deposits, cholesterol, and other substances build up within artery walls. These plaques can narrow the arteries and restrict blood flow.
Diabetes and hypertension increase cardiovascular risk, making it important to manage both conditions.
Increased cardiovascular strain
Increased blood pressure means the heart has to work harder to overcome increased resistance.
Over time this can cause changes to the heart muscle and make it more likely to develop heart failure and other cardiac complications.
Hypertension doesn’t just mean they have one more condition on their list but can increase how much cardiovascular and vascular disease they have on top of their existing diabetes.
How High Blood Pressure Affects the Heart and Blood Vessels
Cardiovascular disease is a major health concern for people with type 2 diabetes.
High blood pressure adds to this risk by placing continued strain on the heart and arteries.
Increased risk of heart disease
The heart has to work harder to pump blood around the body which can cause the heart muscle to become thicker and potentially less efficient.
It also contributes to atherosclerosis meaning you are more likely to suffer from coronary artery disease.
If the arteries carrying blood to your heart become seriously blocked or narrowed it increases your risk of having a heart attack.
Increased risk of stroke
A stroke can occur if there is reduced blood supply to an area of the brain or there is a bleed from a blood vessel.
A key risk factor for both types of stroke is high blood pressure.
People with diabetes already have an increased risk of cardiovascular disease so managing blood pressure is especially important if hypertension is also present.
Increased risk of heart failure
Long-term high blood pressure can cause increased workload on the heart, leading to an enlarged and/or stiff heart which can cause problems with how well your heart pumps or fills with blood.
Diabetes can lead to heart disease via various other metabolic and vascular mechanisms.
Managing blood pressure, blood glucose, cholesterol, and other cardiovascular risk factors can help reduce the overall risk of heart disease and other complications.
The Connection Between Hypertension and Diabetic Kidney Disease
The kidneys are highly susceptible to damage caused by diabetes and hypertension.
There are millions of small filtration units found in each kidney known as nephrons. These help to remove waste products and extra water from the blood whilst keeping the substances that are required in the body.
High blood sugar levels can cause damage to the small blood vessels that are present in the kidneys which can affect their ability to filter the blood.
High blood pressure can cause extra strain on these filtration units and can lead to chronic kidney disease.
What is albuminuria?
Early signs of kidney damage can cause albuminuria.
Healthy kidneys generally retain most proteins in the bloodstream to pass from the blood to the urine. However, when the kidney filters become damaged some albumin can be found in the urine.
Albuminuria can be detected before there is a decrease in kidney function.
Why eGFR matters
Healthcare professionals will also measure your estimated glomerular filtration rate (eGFR).
The eGFR is an estimate of kidney filtration calculated using blood test results, particularly serum creatinine, along with relevant patient information.
For those with diabetes it is important to monitor your Urine Albumin Creatinine Ratio (UACR) and eGFR to ensure early detection and monitoring of kidney disease.
Why controlling blood pressure matters
Effective management of hypertension can help reduce damage to kidneys and slow down chronic kidney disease.
In the 2026 ADA standards of care, it suggests a target blood pressure <130/80mmHg can be used in patients with chronic kidney disease. For some patients with increased cardio-vascular or renal risk more aggressive treatment to achieve lower systolic BP may be appropriate.
Patients with diabetes should discuss any results from kidney testing with their healthcare professional and also what their blood pressure target should be.
How High Blood Pressure Can Affect the Eyes and Other Blood Vessels
There are small blood vessels inside your eyes which carry blood to supply the retina (light-sensitive tissue at the back of the eye).
These can be damaged in diabetes and cause diabetic retinopathy.
Having high blood pressure can put extra stress on the blood vessels and may make further damage more likely.
In some cases, there may not be any noticeable symptoms in the early stages of diabetic retinopathy which is why it is important that you have regular eye tests for diabetes.
Other blood vessel complications
Diabetes and hypertension are important risk factors for peripheral artery disease (PAD), a condition in which arteries supplying the legs and feet become narrowed and blood flow is reduced.
Possible symptoms include:
- Pain or cramping in the legs during walking that improves with rest.
- Coldness in one leg or foot compared with the other.
- Changes in skin colour.
- Slow-healing wounds on the feet or legs.
- Reduced hair growth on the legs.
Some people will not have any obvious symptoms.
It is important to check your feet regularly and attend regular appointments with your medical team especially if you have diabetes and other cardiovascular risk factors.
Insulin Resistance and Hypertension:
Understanding the Connection
One of the key features of type 2 diabetes is insulin resistance.
Insulin resistance means that the cells in the body do not respond efficiently to the insulin, meaning that glucose cannot get into the cells as efficiently, leading to high blood glucose levels.
Insulin resistance often occurs together with hypertension. The link between them is complex.
Several mechanisms may contribute to this connection:
- Kidney sodium handling: Changes in how the kidneys regulate sodium can affect fluid balance and blood pressure.
- Sympathetic nervous system activity: Increased activity of this system can influence heart rate and blood vessel constriction.
- Vascular function: Insulin resistance and metabolic abnormalities may be associated with impaired function of the blood vessel lining.
- Inflammation: Chronic low-grade inflammation and metabolic changes may contribute to cardiovascular and vascular dysfunction.
These can often overlap which helps to explain why hypertension and type 2 diabetes often co-exist.
It is important to remember that not all cases of high blood pressure will be caused by insulin resistance. Genetic factors, age, kidney function, body weight, drugs and other co-existing medical conditions can also contribute.
For more information, read our guide on insulin resistance and its relationship with metabolic health.
What Blood Pressure Target Should People With Diabetes Aim For?
Blood pressure should be tailored based on a person’s health, cardiovascular risk, kidney function, age and treatment tolerance.
In the 2026 Standards of Care by the American Diabetes Association, the target blood pressure should be below 130/80 mmHg whilst on treatment.
For individuals at high cardiovascular or kidney risk, a systolic blood pressure target below 120 mmHg should be encouraged when appropriate and safely tolerated.
Not everyone with diabetes will try to get their blood pressure below 120 mmHg.
People who experience dizziness, falls, or low blood pressure when standing may need a less intensive target.
Understanding blood pressure readings
Blood pressure readings consist of two numbers:
Systolic Pressure – This is the top number. It refers to the pressure within your artery during heartbeats.
Diastolic Pressure – This is the bottom number. It refers to the pressure within your artery between heartbeats.
An example would be 130/80 mmHg (systolic blood pressure of 130 and diastolic of 80).
According to the ADA’s 2026 Standards of Care, hypertension is defined as an average systolic blood pressure of at least 130 mmHg or an average diastolic blood pressure of at least 80 mmHg, based on two or more measurements obtained on two or more occasions.
If you have one high reading it doesn’t mean you will have a diagnosis. Your healthcare professional will consider repeated readings and your overall clinical situation.
How to Monitor Blood Pressure at Home
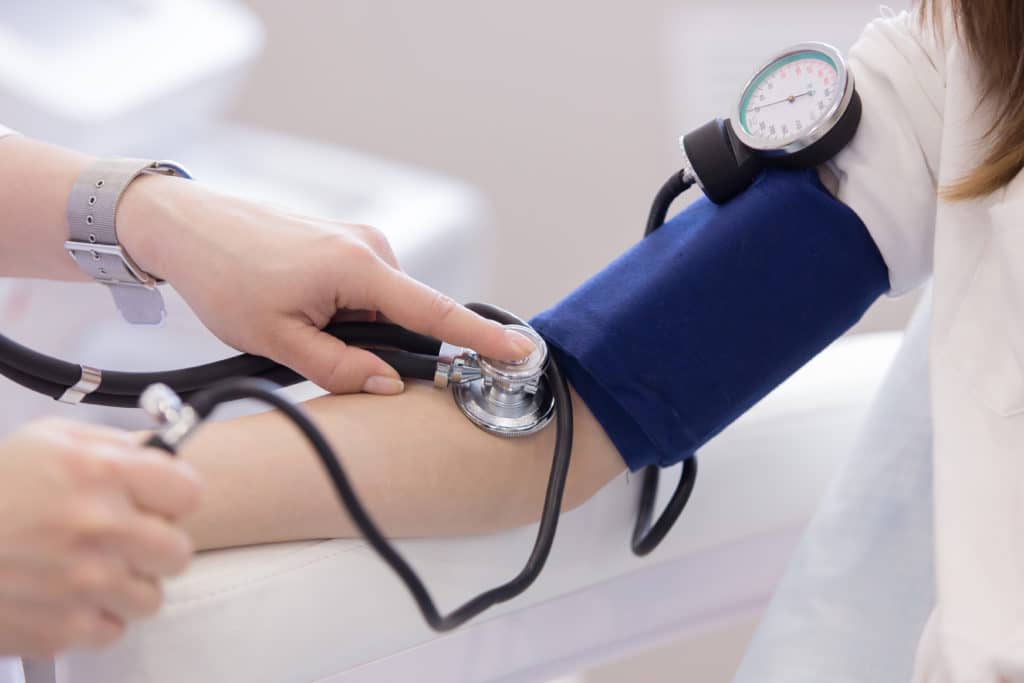
Home blood pressure monitoring can help you and your healthcare professional understand what is happening with your blood pressure between visits.
The ADA recommends that people with diabetes and Hypertension should take their blood pressure at home after proper training.
Some tips to ensure you get a more accurate reading:
Choose an appropriate monitor
Use a validated automatic upper-arm blood pressure monitor with a cuff that is the correct size for your arm.
An incorrectly sized cuff can produce inaccurate readings.
Ask your healthcare professional to check your machine and to show you how to use it if needed.
Prepare before taking a reading
For a more accurate measurement:
- Avoid caffeine, smoking, and exercise for at least 30 minutes beforehand.
- Empty your bladder.
- Sit quietly for at least five minutes.
- Avoid talking, texting, or using your phone during the measurement.
Use the correct sitting position
When measuring your blood pressure:
- Sit with your back supported.
- Keep both feet flat on the floor.
- Do not cross your legs.
- Place the cuff on your bare upper arm.
- Support your arm on a flat surface at heart level.
Record your readings
Take two measurements one minute apart.
Follow your healthcare professional’s advice on how frequently to take your readings.
Don’t alter your medication based on a single reading at home without discussing it with your healthcare team.
Keeping a record may help your clinician to see if your treatment is working and if any changes need to be made.
Managing Type 2 Diabetes and Hypertension Together
Managing both conditions can seem challenging, but a coordinated approach can make it easier. The goal is to improve blood glucose management while also addressing blood pressure and other cardiovascular risk factors.
Follow your prescribed medication plan
Medicines might be needed to manage blood sugar, blood pressure, cholesterol and other risk factors.
Several classes of medication are used to treat hypertension, including:
- ACE inhibitors.
- Angiotensin receptor blockers (ARBs).
- Thiazide-like diuretics.
- Calcium-channel blockers.
The medication prescribed will depend on your blood pressure, kidney function, urine albumin levels, heart/vascular history, other medical problems and possible side effects.
For people with diabetes and hypertension, an ACE inhibitor or an angiotensin receptor blocker (ARB) is recommended when moderately increased urine albumin is present. These medicines are strongly recommended for people with severely increased albuminuria and/or an eGFR below 60 mL/min/1.73 m², when appropriate.
They can help slow kidney disease progression and reduce cardiovascular risk. Kidney function and blood potassium should be monitored when these medicines are started and during treatment.
You may also be prescribed glucose-lowering medicines with cardiovascular or kidney protection benefits. For example, a certain type of SGLT2 inhibitor or GLP-1 receptor agonist.
These will have specific uses and are not a substitute for the treatment of hypertension.
Always consult a healthcare professional before beginning, stopping or altering any medication.
Follow a balanced, heart-healthy eating pattern
Having a healthy, balanced diet can help manage your blood glucose and blood pressure levels.
Some helpful tips include:
- Eating a variety of vegetables and appropriate fruit.
- Wholegrain and high fiber foods.
- Appropriate sources of lean protein.
- Limiting highly processed foods which are high in salt.
- Limiting sugar-sweetened drinks.
- Choosing healthier sources of fat.
One proven way to help manage your blood pressure is the DASH (Dietary Approaches to Stop Hypertension) diet.
If you have chronic kidney disease your requirements may differ. You may need individualized advice on how much potassium, phosphorus, salt and protein to have.
Pay attention to sodium intake
Too much sodium can cause an increase in blood pressure for some people.
Reducing the amount of sodium in processed and packaged foods, sauces and other high-sodium products can help.
Talk to your healthcare professional about what is appropriate for you. If you have kidney disease or are on medication affecting your potassium levels, do not use salt substitutes without talking to a health professional.
Exercise regularly
Physical activity can increase cardiorespiratory fitness and help you manage your weight and become more sensitive to insulin.
You could do:
- Walking
- Cycling
- Swimming
- Resistance exercises
- Other moderate intensity physical activity
The ADA recommend most adults with diabetes should aim to do 150 minutes of moderate to vigorous intensity aerobic activity per week, on at least 3 days. However, you should not go more than two days in a row without activity.
Your physical activity should also consider your overall health and any complications you have from diabetes.
Read more about how regular exercise helps control blood glucose levels.
Maintain a healthy weight
Losing weight can help improve your blood pressure, insulin resistance and blood sugar control if you are overweight.
You do not have to go to extremes.
Making small lifestyle changes such as eating a healthy, balanced diet, getting regular exercise, getting enough sleep and seeking professional advice will generally provide a sustainable method of losing weight.
Manage stress and prioritize sleep
Stress can temporarily raise blood pressure and may make diabetes self-management more difficult.
Try incorporating practical stress-management habits into your routine, such as:
- Regular physical activity.
- Relaxation exercises.
- Maintaining a consistent sleep schedule.
You can also read our guides on how stress may affect type 2 diabetes and starting a diabetes-friendly yoga routine.
Keep up with regular health checks
Managing diabetes and hypertension requires more than checking blood glucose occasionally.
Your healthcare team may recommend monitoring:
- Blood pressure.
- HbA1c and blood glucose.
- Kidney function through eGFR.
- Urine albumin-to-creatinine ratio.
- Blood cholesterol.
- Eye health.
- Foot health.
The frequency of these checks depends on your health and existing complications.
Regular follow-up helps identify changes early and allows your treatment plan to be adjusted when necessary.
Frequently Asked Questions:
Why is high blood pressure dangerous for people with type 2 diabetes?
Having high blood pressure puts extra pressure on the blood vessels and the heart. Having this alongside diabetes can increase the risk of cardiovascular disease, stroke, kidney disease, and damage to the small blood vessels that supply the eye and other organs.
Can having high blood pressure make my type 2 diabetes worse?
Hypertension does not necessarily increase your blood sugar levels but can increase the risk of cardiovascular and vascular complications from diabetes. Managing both of these will reduce the risk of health issues.
What is considered a high blood pressure for someone with diabetes?
According to the ADA’s 2026 Standards of Care, hypertension is defined as an average systolic blood pressure of at least 130 mmHg or an average diastolic blood pressure of at least 80 mmHg, based on two or more measurements obtained on two or more occasions. Your healthcare professional will interpret your readings in the context of your overall health.
What is the target blood pressure for someone with diabetes?
An on-treatment target below 130/80 mmHg is recommended when it can be safely achieved. For individuals at high cardiovascular or kidney risk, a systolic blood pressure target below 120 mmHg should be encouraged when appropriate and safely tolerated. Treatment targets should be individualized.
Can reducing blood pressure help protect my kidneys?
Appropriate blood pressure management can help reduce the risk of kidney damage and slow the progression of chronic kidney disease. For people with diabetes and hypertension, ACE inhibitors or ARBs are recommended when moderately increased urine albumin is present and are strongly recommended in cases of severely increased albuminuria and/or an eGFR below 60 mL/min/1.73 m², when appropriate.
What types of blood pressure medication are commonly used for people with diabetes?
Common medication classes include ACE inhibitors, angiotensin receptor blockers (ARBs), thiazide-like diuretics, and calcium-channel blockers. The appropriate choice depends on kidney function, urine albumin levels, cardiovascular history, blood pressure, and individual treatment needs.
Can exercise help reduce blood pressure and blood sugar levels?
Having regular physical activity can help with managing your blood pressure, increase insulin sensitivity and help with weight management. The right activity and exercise should be done based on your health, fitness and complications.
Should I monitor my blood pressure at home?
Yes. Monitoring your blood pressure can help those with diabetes and hypertension. Ensure you are using a validated machine, measuring correctly and keeping a log. Speak to your healthcare professional about your results.
Can hypertension cause diabetic kidney disease?
Hypertension can cause damage to the kidneys and increase the risk of developing chronic kidney disease. High blood sugar levels and high blood pressure can cause damage to the kidney filters.
What other health issues can occur with diabetes and hypertension?
This can increase the risk of coronary artery disease, heart attack, stroke, heart failure, diabetic kidney disease, retinopathy and peripheral artery disease. This can vary from person to person.
Key Takeaways
High blood pressure and type 2 diabetes frequently occur together.
Both conditions can cause damage to vessels, making it important to maintain good control of your blood pressure along with your blood glucose levels.
Key points:
Hypertension is a significant risk factor for cardiovascular disease and kidney disease in patients with type 2 diabetes.
High blood pressure can lead to damage of the heart, kidneys, eyes and vessels.
Insulin resistance can be related to hypertension. There are many mechanisms at play here.
An individualized blood pressure target should be set. The ADA recommends that your blood pressure should be kept below 130/80 mmHg whilst on treatment if this can be safely achieved.
Keeping a log of your blood pressure at home can be beneficial.
Taking the correct medications, eating a balanced diet, exercising regularly and maintaining healthy habits can help.
Keep an eye on your kidney function and albumin in your urine.
Regular appointments with your healthcare professional will be important.
Overall it is important to take a holistic approach and keep your blood glucose, blood pressure, cholesterol, kidney health and lifestyle under control to help reduce the risk of complications.
Educational Notice
This article is provided for educational purposes only. It does not replace professional medical advice, diagnosis, or treatment.
Do not start, stop, or change diabetes or blood pressure medication based on this article. Blood pressure targets and treatment decisions should be individualized by a qualified healthcare professional.
Learn more about our standards:
Recommended Reading
- How to Use a Continuous Glucose Monitor (CGM) to Track Blood Sugar
- How Regular Exercise Controls Your Blood Sugar Levels
- How to Improve Insulin Sensitivity by Optimizing Sleep Duration
References
- American Diabetes Association. 10. Cardiovascular Disease and Risk Management: Standards of Care in Diabetes—2026.
- American Diabetes Association. 11. Chronic Kidney Disease and Risk Management: Standards of Care in Diabetes—2026.
- American Diabetes Association. Summary of Revisions: Standards of Care in Diabetes—2026.
- American Heart Association. Home Blood Pressure Monitoring.
- American Heart Association. Home Blood Pressure Measurement Instructions.

admin
All Posts